Clonal haematopoiesis of indeterminate potential (CHIP)
2 These include: A ME/CFS-like phenotype with post-exertional malaise and impaired bioenergetics A dysautonomia/POTS-dominant presentation A mast celldriven inflammatory phenotype Persistent cardiopulmonary injury This heterogeneity explains why a single treatment approach fails
Napping cant replace poor nighttime sleep, but a short half-hour nap can help improve mood, alertness, energy levels, and performance
Our experience working with researchers in this space shows that severity-matched dosing matters more than aggressive dose escalation

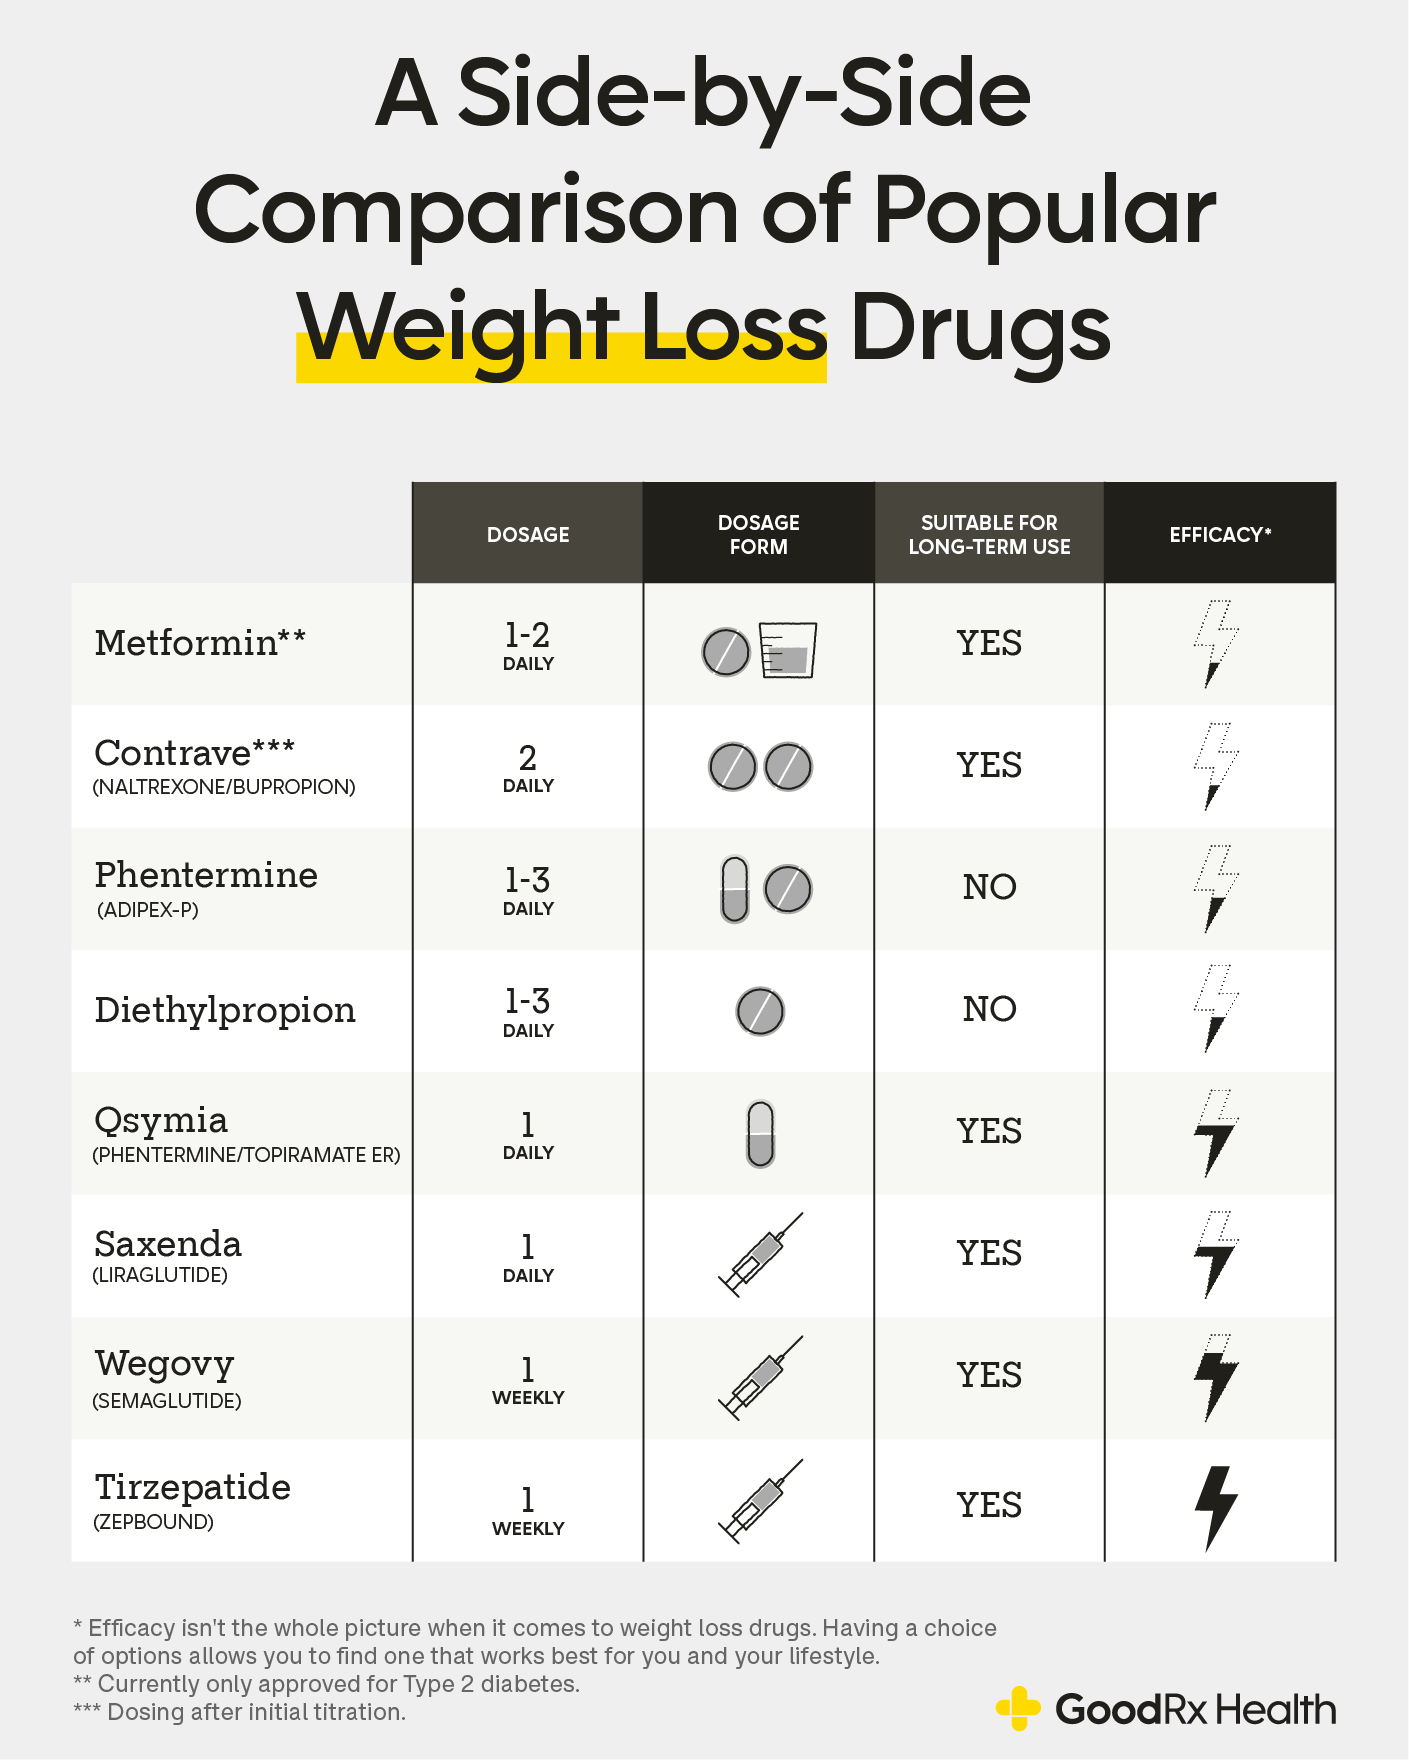
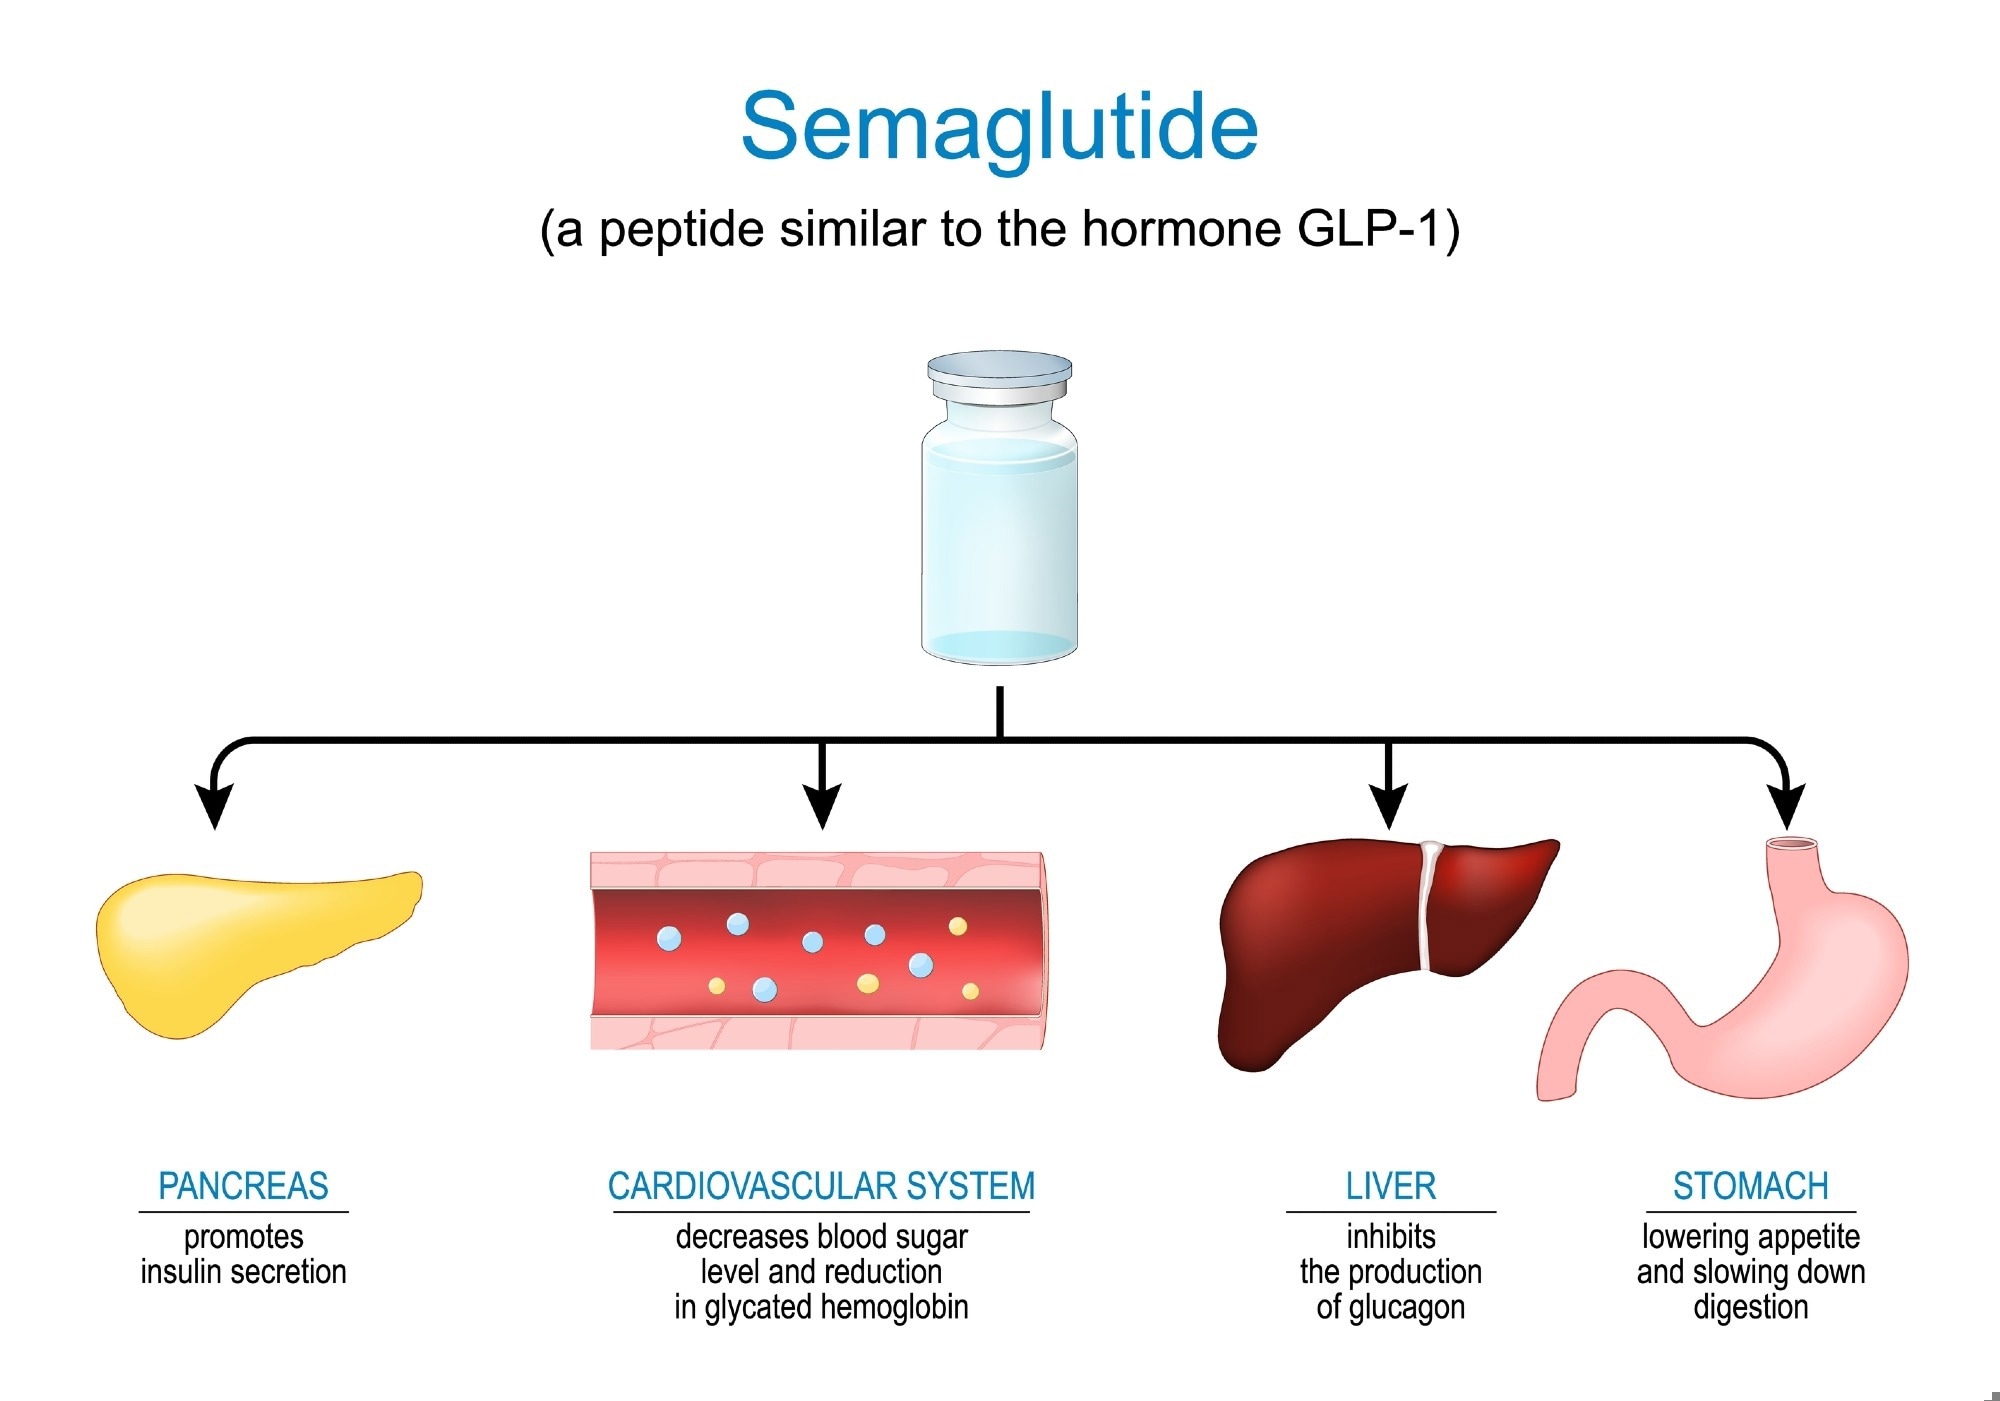
Further weight loss (1015 kg) extends benefits to conditions like sleep apnoea, acid reflux, and osteoarthritis while exceeding 15 kg is strongly linked to type 2 diabetes remission and improved cardiovascular function.[17] Approved anti-obesity medications, like orlistat, liraglutide, naltrexone-bupropion, and phentermine-topiramate, offer modest weight loss (35 kg).[17] Liraglutides 3 mg/day injection leads to an 8% reduction after one year.[18] Semaglutide achieves up to 16% weight loss with a weekly 2.4 mg subcutaneous injection over a year.[19,20,21] Tirzepatide, a dual GIP and GLP1RA, exhibits an 11.9% to 12.4% weight reduction at 10 mg and 15 mg doses per week over 618 months.[22,23] In this context, our meta-analysis highlights the impressive weight loss achieved with cagrilintide-based therapies, particularly with cagrisema 2.4/2.4 mg, which was noted to be superior to semaglutide 2.4 mg in terms of both percentage and absolute weight loss over a 6-month clinical use period, albeit at the expense of increased gastrointestinal side effects
Most of this research is still early-stage and often funded by the companies behind specific branded ingredients, so treat any single dramatic multiplier with healthy skepticism but the underlying mechanism is sound, established pharmaceutical science, not a marketing invention