When a tissue is injured, whether it's a tendon, muscle, or even skin, the first thing it needs for repair is a robust blood supply
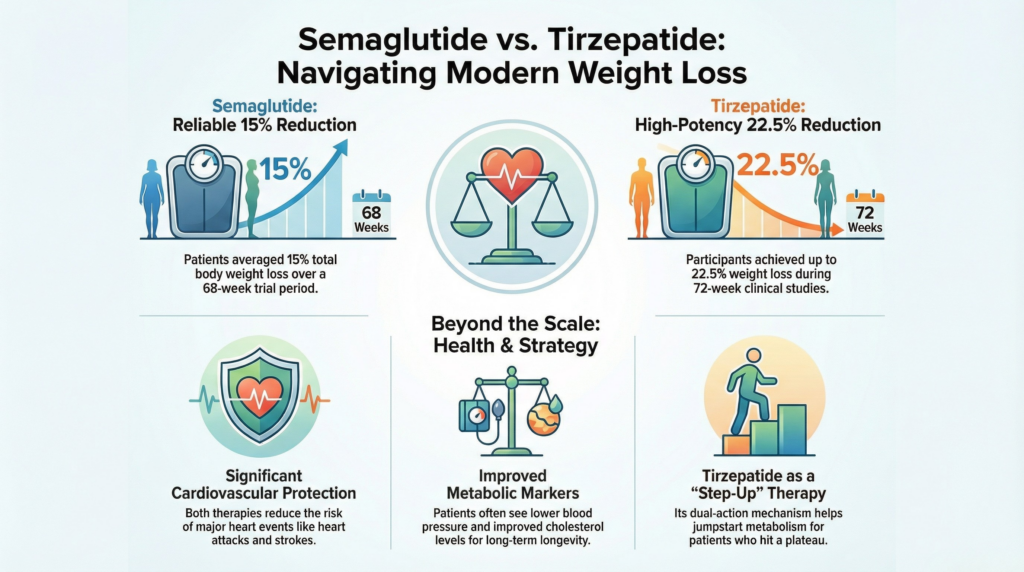
Studies have also linked the drugs to a host of other benefits, including a lower risk of heart attacks, strokes, dementia, clotting disorders, addiction and sleep apnea
Importantly, these voluntary discontinuations were based on perceived satisfactory results rather than inadequate weight loss, minimizing potential bias

Heres a good general approach: A good rule of thumb is that bleeding that is lighter than the patients usual menstrual period is reassuring Bleeding heavier than menses should make you pause, consider US imaging, and definitely consider a pelvic exam (see below) And true heavy bleeding is when the patient soaks through a maxi-pad per hour for more than 2 hours this is concerning bleeding requiring a pelvic exam, imaging, intervention, and usually OB/Gyne consultation Other vaginal symptoms (including abnormal discharge or symptoms of infection) Pain or cramping (including severity and location) Symptoms of hemodynamic compromise (like dizziness, orthostasis, and syncope) Past obstetric, medical, and surgical histories, including history of previous pregnancy loss, ectopic pregnancy, and use of assisted reproductive technology And the key points on your physical exam : Vital signs Abdominal exam Red flags = unilateral tenderness, palpable adnexal mass, peritonitis Pelvic exam do we need to do it

Warming semaglutide is unnecessary and potentially counterproductive
Rapid shifts in blood glucose levels and changes in salt and water retention may trigger tension or vascular-type headaches as the body recalibrates its metabolic state