Journal of Strength and Conditioning Research, 21(1), pp.259-264
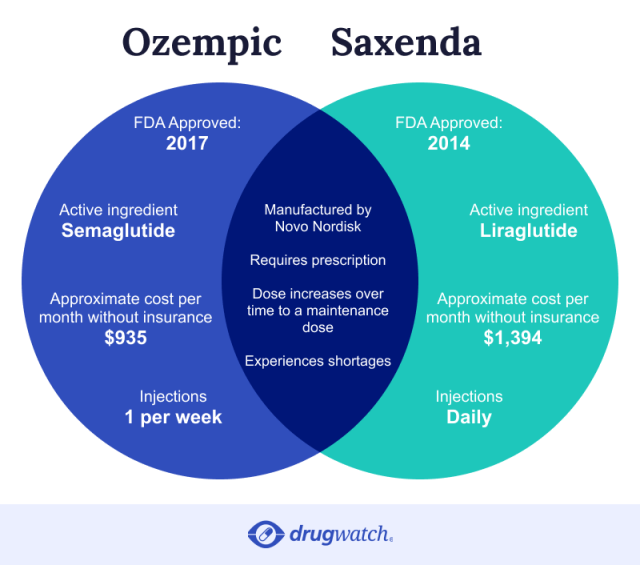
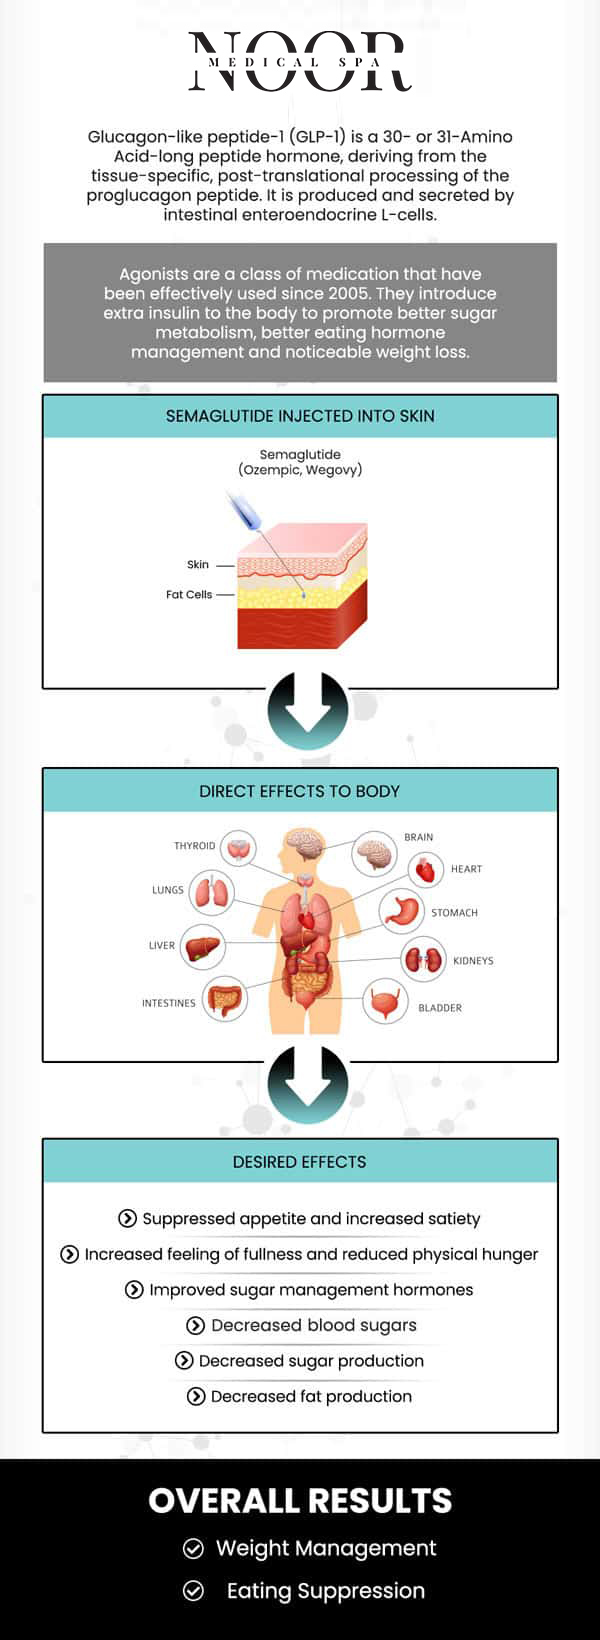
Many on staff have personally used GLP1 medication, which helps them better relate to patients
European research institutions frequently employ peptide blends when studying complex molecular signalling networks that require simultaneous peptide-driven inputs
The report covers detailed analysis of 40+ countries and the top five countries have been shared as a reference
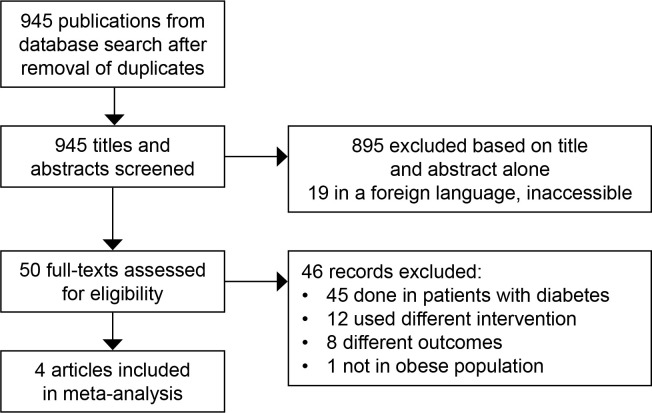
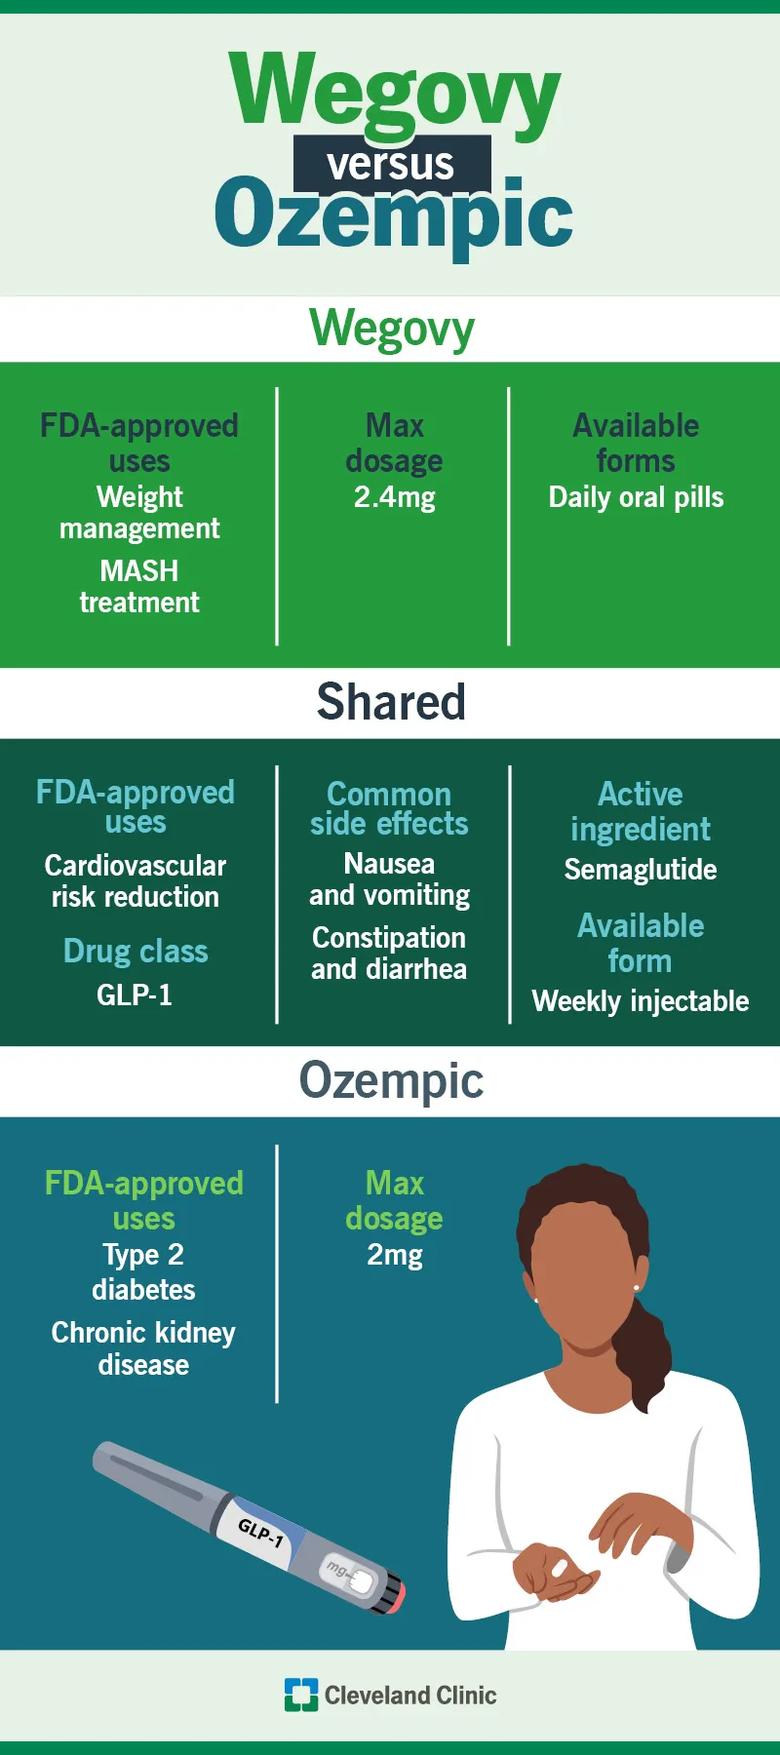
What the study found In patients with obesity + HFpEF, semaglutide and tirzepatide showed similar rates of: all-cause death HF hospitalization and the composite outcome (death + HF hospitalization) Key numbers TriNetX federated EHR analysis 3,983 patients total 1:1 propensity-matched: 1,258 vs 1,258 Median follow-up: 24 weeks Primary composite outcome: HR 1.14 (95% CI 0.891.46), p=0.286 My take For cardio-obesity HFpEF care, this is a useful reminder: Drug selection is often aboutthe right patient, the right goal, the right contextnot just which agent gives more weight loss. So in practice, choice may be driven by: tolerability access/cost glycaemic needs comorbidities patient adherence preferences Important caveat: this is retrospective observational EHR data (not a randomized head-to-head trial), with short follow-up
A natural way to Burn Fat, Himalayan Organics L Carnitine Tablets